All in - 30/09/2026
All in - 30/09/2026
Hip Arthritis Symptoms: Where It Hurts and What Helps
The common signs, how it differs from pain on the side of the hip, and what to do next.
READ MORE

The first few steps of the morning are the worst part of the day, then it eases off. That pattern has a name, it gets busier every spring, and it responds to almost the opposite of what most people do about it.
It usually starts as a bruised feeling under the heel that you notice getting out of bed. The first three or four steps to the bathroom are sharp, then it warms up and you mostly forget about it.
Until you stand up after a long meeting, or get out of the car after school pick-up, and there it is again.
If that’s you, you’re in good company. Plantar heel pain (you may know it as plantar fasciitis) is the most common cause of heel pain we see in clinic. It’s most common between 40 and 60, and it has a season. September is the start of it.
Running from your heel bone to the base of your toes is a thick band of connective tissue called the plantar fascia. It holds up the arch of your foot and works like a spring, storing energy as your foot flattens on each step and giving it back as you push off.
Where it attaches to the heel bone, it takes a lot of load. When that load rises faster than the tissue can adapt to, the attachment gets irritated, a little thickened and a lot more sensitive.
It’s not really an inflammation, despite the name. Under the microscope it looks like a tendon that’s been asked for more than it was ready for, which is why researchers now call it plantar fasciopathy rather than fasciitis.
Tissue that’s been overloaded doesn’t recover by being ignored. It recovers by being loaded properly.
Overnight your foot rests pointed slightly downward, so the fascia sits in a shortened position for seven or eight hours and stiffens. Your first step out of bed stretches it suddenly, under your full bodyweight, before it’s had any warning.
A few minutes of walking and it’s warmed up and lengthened, and the pain settles. The same thing happens after any long stretch of sitting.
That pattern, sharp on the first steps and easing with movement, is the tell. It’s what we listen for when someone describes their heel, and it’s the main reason most people don’t need a scan. A heel spur on an X-ray is common, sits in plenty of feet that don’t hurt at all, and isn’t the cause of the pain.
Almost every heel we see in September has a story that begins with a change. A new walking route with a hill in it. A return to running after a quiet winter. A weekend on your feet at netball or the football. A holiday spent walking all day in sandals.
The things that make a heel more likely to complain are fairly consistent:
None of those is a character flaw. They’re load arriving faster than the tissue could keep up with.
Rest is the instinct, and rest on its own is the thing that keeps this going for a year. A large proportion of people still have symptoms two years after diagnosis, and in our experience they’re usually the ones who waited for it to go away, then went back to the same load and got the same result.
Here’s what the evidence supports instead.
With a plan like that, most heels are noticeably better within six to eight weeks and keep improving over the following months. The strengthening is what makes it stay better.
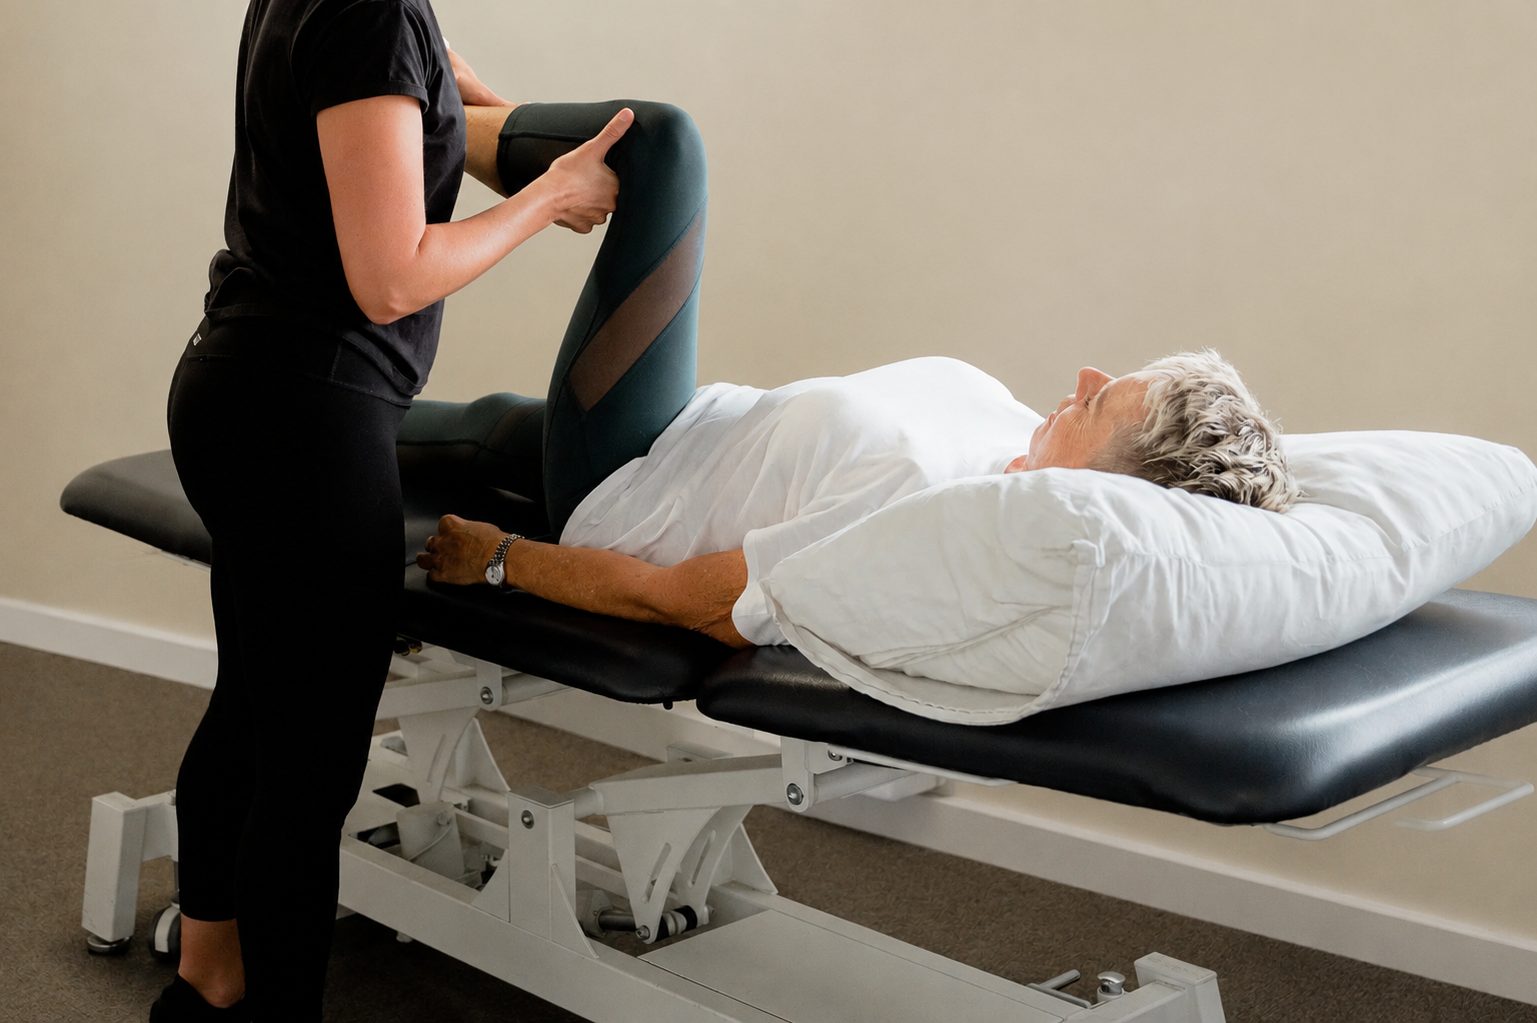
If your heel follows the first-step pattern and it’s been there for more than a couple of weeks, that’s exactly what a physio assessment is for. We work out what’s actually driving it and build the plan around that. The people who get on top of this quickly are the ones who come in early, before the tissue has had months to dig in.
Come in sooner if any of these apply:
The work itself is fairly low-drama. An assessment looks at how your calf, ankle and foot are working together, what changed in your load, and what you’re wearing on your feet. From there the plan is built for what your body needs, and you keep walking while it heals.
Heel been sore for more than a couple of weeks?
Our physios see this every spring. We’ll meet you where you’re at, and help you build from there.
All in - 30/09/2026
All in - 30/09/2026
The common signs, how it differs from pain on the side of the hip, and what to do next.
READ MOREPrefer to talk? Yarraville (03) 8319 9945 · Hampton East (03) 9086 3740 · Kensington (03) 8319 9946
Please don’t include medical or health information in this form. For clinical questions or appointments, call your studio or book online. Your message goes straight to the studio you choose.
This site is protected by reCAPTCHA and the Google Privacy Policy and Terms of Service apply.

Specialist care from physios who truly understand women’s bodies.

Senior Women’s Health Physiotherapist
Emily has a deep passion for empowering women to take control of their pelvic health. She creates a warm, judgement-free space where you can talk openly about what’s really going on.
With advanced training in pelvic floor rehabilitation, Emily treats a wide range of conditions including incontinence, prolapse, pelvic pain, and pregnancy-related concerns. She takes the time to really listen, explain what’s happening in your body, and build a treatment plan that fits your life. Whether you’re preparing for birth, recovering postpartum, or navigating menopause — Emily is here to help you feel strong and confident again.

Women’s Health Physiotherapist
Tori is passionate about helping women feel heard and supported through every stage of life. She combines clinical expertise with genuine empathy to deliver care that makes a real difference.
Tori brings a holistic, evidence-based approach to treating pelvic floor dysfunction, pregnancy-related pain, and postnatal recovery. She has a special interest in helping women return to exercise safely after having a baby and supporting those with persistent pelvic pain. Tori believes every woman deserves to understand her body and feel empowered in her recovery — no topic is too awkward, and no concern is too small.